

Immunotherapy-related arthritis happens when certain cancer treatments trigger immune activity that inflames your joints. Tell your oncology team about new joint swelling, persistent stiffness, or pain that makes ordinary tasks difficult.
Cancer treatment already asks so much of you, and another symptom can bring another worry. Early attention can help protect your movement while your doctors plan how to continue treating the cancer. Begin by noticing what has changed, including the small things your hands and feet once did without effort.
Key Takeaways
- New swelling or stiffness during checkpoint inhibitor treatment deserves a call to your oncology team, even after treatment ends.
- A suddenly hot, painful joint needs urgent assessment, especially with fever, because infection can resemble treatment-related arthritis.
- Treatment depends on how much inflammation affects daily life. Your oncology and arthritis specialists should make medication decisions together.
- Arthritis can persist after immunotherapy stops, but its presence doesn’t mean the cancer has returned.
Recognizing Immunotherapy-Related Arthritis
Immune checkpoint inhibitors help the immune system attack cancer by removing some of its natural brakes. Their effects can also reach healthy joint tissue, causing ICI-induced arthritis, one form of the immune-related adverse events these medicines can cause.
These medicines include treatments targeting PD-1, PD-L1, and CTLA-4, such as pembrolizumab, nivolumab, and ipilimumab. Our explanation of how cancer immunotherapy works describes how checkpoint inhibitors differ from other immune-based treatments.
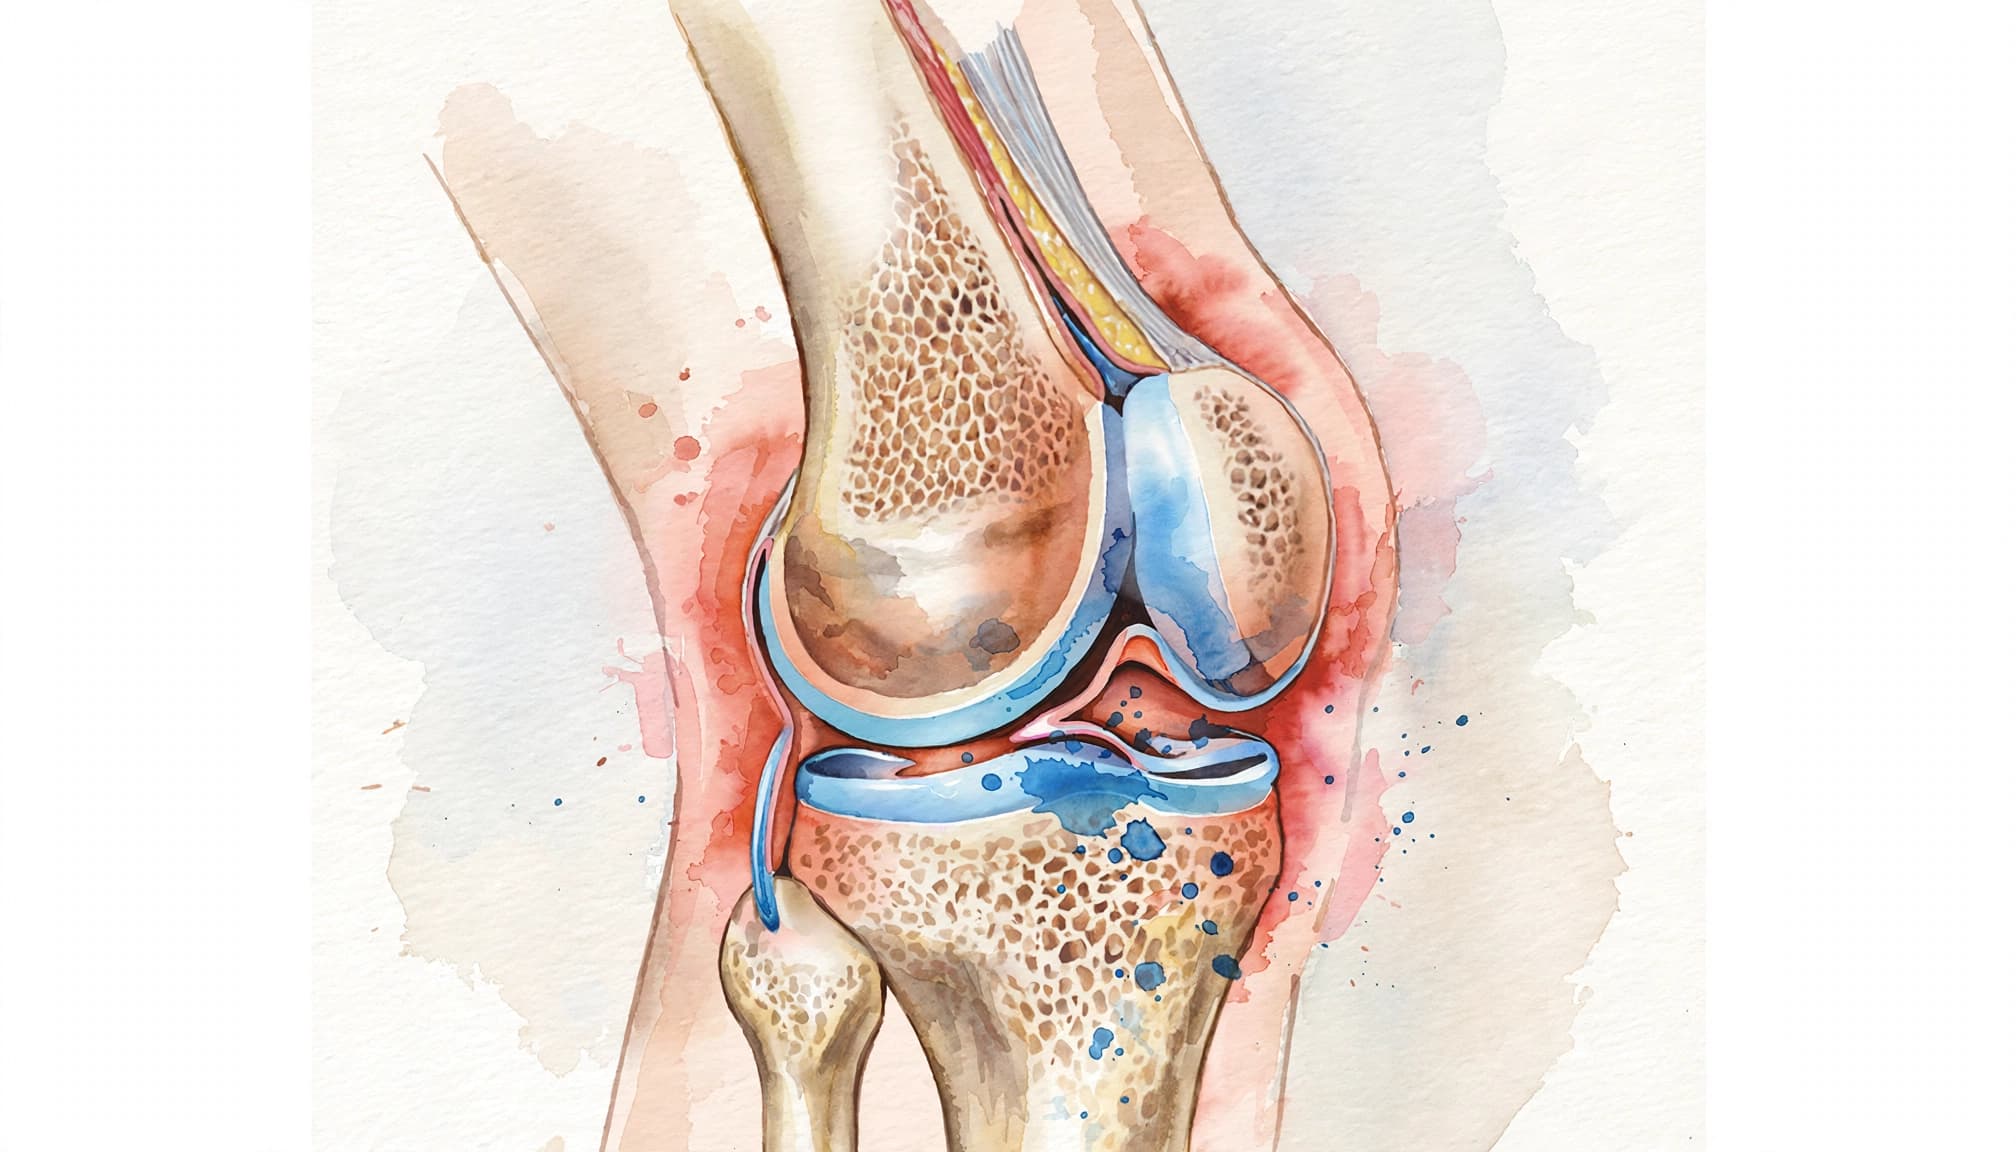
Joint pain versus joint inflammation
Doctors call joint pain alone “arthralgia.” Inflammatory arthritis involves inflammation within the joint, which may cause swelling, warmth, tenderness, and restricted movement.
Stiffness often feels worse in the morning or after sitting. You might struggle to close your hand, fasten buttons, or take those first steps after resting. Pain alone doesn’t tell your team which problem you have.
How it differs from rheumatoid arthritis
The symptoms can resemble rheumatoid arthritis, including swelling in several small joints. Many people with checkpoint-related arthritis are seronegative, meaning they lack rheumatoid factor and anti-CCP antibodies, blood markers often found in that condition.
Negative results don’t rule out joint inflammation. Rheumatoid arthritis can also occur without these antibodies, so your examination and symptom history matter more than a single blood test.
How Common Is It, and When Does It Begin?
Reviews estimate that inflammatory arthritis affects about 1% to 7% of people receiving checkpoint inhibitors in clinical trials. Estimates vary because studies use different definitions and don’t always capture joint symptoms consistently.
Joint pain occurs more often than confirmed arthritis. Published estimates range widely, reaching 43% in some reports. That figure includes pain without proven joint inflammation.
Timing also varies. One systematic review found a median onset of four months, while another review reported 2.8 months. Symptoms can begin early, much later, or after treatment stops.
A 30-patient Johns Hopkins study found different patterns. In that small study, combination therapy targeting CTLA-4 and PD-1 more often began with knee arthritis. Treatment with one checkpoint inhibitor more often began in smaller joints. Neither pattern proves the diagnosis, but each gives your team useful information.
When to Call Your Oncology Team
You don’t have to decide whether your symptoms deserve an arthritis diagnosis before asking for help. A change in your ability to move is enough to begin the conversation.

Call promptly about new or worsening symptoms
Contact your team about new swelling, persistent morning stiffness, or pain that interferes with walking, cooking, dressing, or sleep. Call the same day if symptoms worsen quickly or you struggle with basic self-care.
Keep a simple record of which joints hurt, when symptoms began, and how long stiffness lasts. Photographs can help show swelling that comes and goes. Don’t postpone a call while gathering this information.
Get urgent help for warning signs
A suddenly hot, red, very painful joint needs urgent medical assessment, especially with fever. Infection or crystals within a joint can cause similar symptoms and require different treatment.
Seek emergency care for chest pain, breathing trouble, or severe new weakness, particularly difficulty swallowing or walking. Other immune-related reactions can affect the heart or muscles. Don’t assume arthritis explains every new symptom.
The four-week referral threshold isn’t a reason to wait four weeks before reporting swollen joints.
What Your Care Team Will Look For
Your clinician will examine the joints, ask about stiffness, and assess how symptoms affect daily activities. Blood tests may help measure inflammation, but normal results don’t settle every case.
Ultrasound or other imaging can reveal inflammation that an examination doesn’t fully show. A clinician may remove fluid from a swollen joint to look for infection or crystals.
Your team also considers other explanations, including ordinary wear-and-tear arthritis, injury, medication effects, and cancer involving bone. Reactive arthritis is another possible cause a clinician may consider. New pain doesn’t automatically mean cancer progression.
ASCO’s arthritis guidance supports early rheumatology involvement for joint swelling or symptoms lasting more than four weeks. A rheumatologist is a doctor who treats inflammatory joint conditions.
Referral matters sooner when symptoms interfere with everyday life or treatment doesn’t control them. Tell both teams about every medicine and supplement you take, including pain relievers you buy without a prescription.
How Doctors Treat the Joint Inflammation
Your doctors match treatment to the severity of inflammation and its effect on daily life. Clinicians decide whether corticosteroids are appropriate. Don’t start steroids, change doses, or stop immunotherapy yourself.
ASCO’s treatment recommendations describe a stepwise approach.
Mild symptoms
For mild arthritis, clinicians may recommend NSAIDs, which reduce pain and inflammation.
They aren’t safe for everyone. Kidney problems, stomach bleeding, blood thinners, and other cancer treatments can affect the choice. When one or two joints cause most of the symptoms, a clinician may consider an intra-articular steroid injection.
Moderate or severe symptoms
When arthritis limits activities such as shopping or preparing meals, clinicians may prescribe prednisone, often 10 to 20 milligrams daily. Your oncologist may temporarily pause immunotherapy.
Severe arthritis that limits basic self-care may require prednisone at 0.5 to 1 milligram per kilogram of body weight daily. These are clinician-directed treatment ranges, not instructions for home dosing.
Your team will plan a gradual dose reduction as inflammation improves. Don’t stop prednisone suddenly.
Persistent symptoms
If arthritis continues or returns during steroid reduction, a rheumatologist may add medicine that controls the underlying inflammation. Options include methotrexate and, for selected patients, TNF inhibitors, a class of anti-TNF medicines such as adalimumab or infliximab.
For selected persistent cases, a specialist may consider tocilizumab. The REACT trial investigated tocilizumab for immune checkpoint inhibitor-related arthritis; its findings haven’t established the drug as standard care.
These treatments need monitoring for infection and other side effects. Your team will weigh how quickly you need relief, your cancer treatment plan, and the risks of continued steroids.
Can Arthritis Treatment Affect Cancer Control?
When you face a life-threatening disease, another prescription can raise a difficult question: will easing the joint inflammation weaken the treatment helping you live?
A small Johns Hopkins study offered some reassurance. Patients who had responded to immunotherapy maintained their cancer response during arthritis treatment. That finding doesn’t prove that every immune-suppressing medicine leaves cancer control unchanged.
A later observational study, discussed in a review of checkpoint-related arthritis, linked certain targeted arthritis medicines with a shorter time to cancer progression than methotrexate. An observational link doesn’t prove that those medicines caused progression; patients receiving them may have differed in important ways.
The decision belongs with oncology and rheumatology together. They should consider your cancer response, joint damage risk, infection risk, and need for symptom relief. You shouldn’t have to choose alone between protecting your movement and treating your cancer.
What Happens After Immunotherapy Stops?
Arthritis doesn’t always disappear when checkpoint treatment ends. Persistent or recurrent arthritis can continue after the medicine leaves your treatment schedule.
In a Johns Hopkins follow-up cohort, 70% of patients who returned for assessment still had active arthritis three months after stopping immunotherapy. At six months, 48% still had active disease. Those figures describe that follow-up group, not everyone who develops this side effect.
Cancer remission and ongoing joint symptoms can exist together. Joint symptoms that persist or return don’t mean cancer has returned. Keep following up with your care team about them.
The emotional adjustment deserves attention, too. Our reflections on finding steadier ground after diagnosis recognize how relief and uncertainty can share the same day. You can welcome reassuring results and still ask for help with pain.
Frequently Asked Questions
Can I restart immunotherapy after arthritis improves?
Sometimes. Your oncologist may consider restarting treatment after symptoms improve and your need for steroids decreases. The decision depends on your cancer, the severity of the arthritis, other immune-related side effects, and available treatment options.
Arthritis can return after treatment resumes, so your teams should agree on follow-up and a plan for worsening symptoms. A temporary treatment pause doesn’t always mean a permanent stop.
What can I do at home while awaiting assessment?
Use gentle movement within your comfort range, and avoid forcing a swollen joint through painful exercise. Rest between activities rather than trying to complete everything at once.
Ask your team which pain medicine suits your treatment and medical history. Our guidance on supportive care during cancer treatment addresses the broader burden of side effects. Home comfort measures should support medical assessment, never delay it.
Your Comfort Belongs in Cancer Care
There is courage in naming a new symptom when part of you hopes it will disappear. Reporting swelling or stiffness gives your team a chance to protect the ordinary movements that matter to you.
Ask for help early, and let oncology and rheumatology build the treatment plan together. Your ability to dress, walk, rest, and reach for someone you love belongs in that plan.
